Tuesday, February 15, 2011

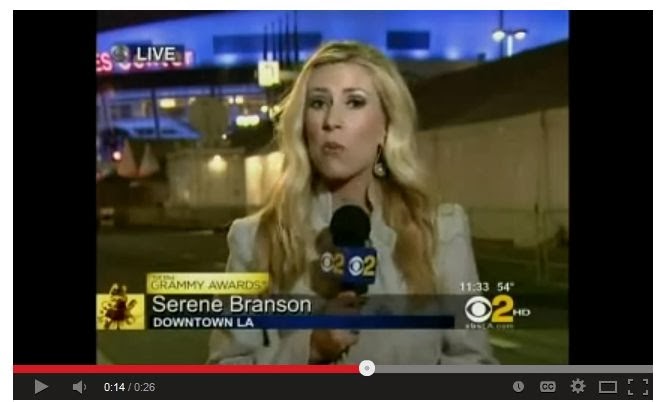
Reporter has TIA on air.

Stroke can rear its ugly self in so many ways. Aphasia is one way. Many thought this was an example...

http://www.youtube.com/watch?v=dwHpBwAxDIs


Further info from the Associated Press

"LOS ANGELES -- The CBS-TV station in Los Angeles says a reporter who spoke incoherently during a segment on the Grammy Awards is feeling fine.


Serene Branson was checked by paramedics immediately after her Grammys report Sunday from outside the downtown Los Angeles arena where the awards where held, according to the station's website.

The young woman's vital signs were normal and she wasn't hospitalized, CBS said. A colleague took her home as a precaution and she said she was "feeling fine" Monday, according to the channel. "

She told her local CBS station last week, "My head was definitely pounding and I was very uncomfortable and I knew something wasn't right. I was terrified and confused. Confused. What had just happened? At that point they sat me down, then my right cheek went numb. My right hand went numb and I lost some sensation in my arm."

Can't talk? Right side numb with no sensation? Its a "complex migraine"? Really? Really?

This lady went through the same thing...


Friday, February 11, 2011

Diet Stroke?

My friend Todd hipped me to this... Do diet sodas cause vascular disease and stroke?

The popular media has decided this study was "dubious" because corporate sponsors told them so.

And "Diet Stroke?" is the perfect headline, right? But no other headlines picked "Diet Stroke"...?

Hmmm... wonder why.


Friday, February 4, 2011

26 months

In my book I talk about "super survivors" defined as a survivor who is “…so unwilling to let go of their career, their independence, or a personal passion that they are compelled to recover. They intertwine recovery with what they love to do.” When somebody can use their life's passion to drive recovery everything is made easier.

  • It's easier for the therapist because they don't have to work so hard to motivate.
  • It's easier for the stroke survivor because they have a cherished task on which to focus.
  • It's easier for the survivor’s brain because when it comes to driving plastic changes "the power is in the focus.” And we tend to focus on what we care about.

There are other things that motivate survivors towards recovery. Things like career (and by extension money), fear (i.e. falling), friendship (many survivors talk about friends who have "ditched" them after their stroke), the need for independence etc. etc. All of these can be extraordinarily important, although I would suggest that they may be somewhat less important than the goals of the "super survivor" focused on a cherished task. But if the scale goes from "I need to get better because of friends, money, fear etc." to “I need to get better in order to get back to guitar playing (a cherished task)" there is actually one step further. That step is called Kathy. Kathy Spencer is the only survivor I know who has reached a “nirvana of recovery”.

People who get really good at stuff are not necessarily completely focused on outcomes. Most folks who become expert at something are focused on process. The goal in great musicians and athletes and students etc. is to learn. To learn is to forcibly rewire the brain. Relearning of movement after stroke is learning, called motor learning. I’ve discussed this before; learning new movements and learning French, piano, math or anything else is the same. They all happen through rewiring existing neurons in the cortex of the brain.

Learning ain’t easy. It necessarily takes work. But let me ask you this…Which student is going to get a better grade…

Jack: “I’m studying because I want a good grade.”

Jill: “I’m studying because this stuff is really cool.”

Outcome focused Vs. process focused.

Obviously the lines can get blurred because as more ability you have the more that can be done to achieve the outcome. But survivors spend much of their time in a no-mans land where they are working, but are not yet able to use their limbs functionally. And this is where the plot is often lost. If your only interest is the outcome you’ll probably say “the outcome is so far away and I may not get there.” If your interest is process the question is, “What can I do to get just a little bit more?

It seems to me like Kathy Spencer fell in love with the process. And it's tough to fall in love with the process that, unlike practicing soccer and guitar, had no guarantee for success, and where you’re not learning anything new, really. With Kathy it seems to be a leap of faith, although as you'll see faith may have had a bit to do with it. In the video below Kathy explains a little bit about the process she went through to recover. What is interesting to me is, not so much the particular exercises she did (these will be different for every survivor) but the perspective she takes. 26 months of hard work during which there was no guarantee.

26 months.

And yes, she mentions my book but I pinky swear, I was going to blog on this within the first 20 seconds of watching this great vid.

Thursday, February 3, 2011

VOTE!


I'm a fan of Dean's Stroke Musings. There is a bunch of information for folks interested in the nexus of stroke recovery and neuroplasticity. He writes from a hardened position of someone who has been there and back looking for some legitimate change among the wooden nickles.


Please feel free to vote for his blog in the catigory of Best Medical Weblog in the patient category in the 2010 Medical Weblog Awards, hosted by Medgadget.


Monday, January 31, 2011

RATS!

Its all about the hand.
F
or anyone interested in evidence-based stroke recovery treatment options, the lower extremity offers a much smaller palette than the upper extremity. Simply, there are a lot less evidence-based treatment options for the lower extremity.

One of the reasons this is true is because the ankle foot orthosis is an effective way of providing compensation for the deficits in gait after stroke. Another reason is that canes and walkers are also extraordinarily effective at compensating for gait deviations and deficits poststroke.


There are other reasons. For instance, there is the general consensus among therapists that what comes back first is the leg, and later on the arm and hand. This is a classic gotcha question for therapists teaching students. "What comes back first the upper or lower extremity?" The wise student will say
the politically correct answer; the lower extremity. But this is not necessarily true. We tend to focus very much on hand and all its intricate movements, especially finger extension. But in the lower extremity we don't typically look at the analog of finger extension: toe extension. Why does nobody care about toe extension? Simple: The toes are hidden by the shoes. Also, toe extension is not essential to a functional gait. Toe extension which helps raise the ankle is compensated for by the ankle foot orthosis.

Another reason for the near myopic focus on the upper extremity is that it's more interesting. The shoulder has more range of motion in more planes and pivots than it's analog the hip. But but more movement in the shoulder is small potatoes.

The main reason for the focus on the upper extremity is the hand. Even before brain imaging the hand fascinated researchers. This delicate instrument at the distal end of the limb drives clinical rehabilitation research related to stroke. There is a common belief that if you can get the hand "back in the game" and somehow get the hand
to grasp release every other aspect of the upper extremity will come back naturally. This is because the entire upper extremity is there at the behest of the hand. You could further argue, although a bit of a stretch, that the reason we walk is to get the hand where it needs to go so that the hand can do what it needs to do.

But there's another huge reason. The brain. The swath of real estate that hand takes up on the brain is huge. The point to point representation of the brain is called the homunculus. The hand takes up almost as much room as the entire face! The face! Where our mouth is! Whe
re our eyes are! Where are ears are! Our identity! When it comes to the brain the hand is, quite literally, huge.

Enter neuroscience, almost all of whom focus on the brain. Neuroscientists are fascinated with the hand for a few reasons. First of all, because of its delicacy, if you figure out the hand the rest of the body is easy. If you are interested in motor learning there's no better laboratory than the hand.

But there may be another reason that neuroscientists are fascinated with the hand. Imagine if you doing clinical research on stroke survivors. They all are different ages, have had their
stroke in different parts of their brain, they're all in different physical shape, they all have different diets, they all have different sequelae, etc. etc.

Now imagine you're doing research and you can have as many study participants as you want and they all have a stroke in exactly the same spot, be the same age, eat the same diet, wake up at the same time in the morning, always show up on time and that you can easily blind (not let them know which group there in) and are genetically related!


Where can you find such study participants? Rats! (And mice) But why rats and mice? Why are rats and mice so important to the equation of figuring out the science of motor learning in the hand? Here's why...


Freaky, huh?

Friday, January 28, 2011

"Best New Medical Weblog"!


I am very happy to report that one of my favorite websites ever
Medgadget has nominated the Stroke Recovery Blog as a "Best New Medical Weblog"!

Also, this is the perfect time to tell you about Medgadget. It really is a cool site. It is a one-stop portal to emergent technology in medicine. For stroke survivors it is a good place to go every once in a while. There is a drop-down menu on the right side of the website which has an entry for "rehab".

Alternatively, you can put something like "stroke rehabilitation" into the search box. If you do that
one such entry involves our team at the Drake Center rehabilitation hospital here in Cincinnati.

Saturday, January 15, 2011

Tools, Techniques and Technology


I do a lot of seminars on driving cortical neuroplastic change, one of the unequivocal bedrocks of recovery, in stroke survivors. I've done talks in some of the best rehab hospitals in this country. I've also done talks in rural areas where the nearest rehab hospital is hundreds of miles away. Some of the attendees have access to a smorgasbord of leading-edge technologies. Some home care therapists have access to very little technology. And whatever technology they do have has to fit in the car. Some have immediate access to neurologists and physiatrists. Other's laugh when I say "Kick it upstairs to physiatry." "We rarely see any doctors,” they say. Rehab settings run the gamut; feast or famine or somewhere in between.
When I do talks I always remind myself of a particular touchstone that reminds me of why I, again and again, get up in front of therapists in the first place. It goes something like this: "If I was a stroke survivor knowing what I know about stroke recovery, what would I want therapist to know?" This question has served me well. I challenge clinicians as an informed advocate.
There are people, facilities and technologies that are essential to achieving the highest level of recovery. It is unfortunate that many facilities and therapists don’t have accesses to these tools. Stroke is the leading cause of long term disability. Recovery deserves the best tools. The clinical expertise is there. Clinicians spend a tremendous amount of time, energy and money being trained to be the best they can be. But just like every other profession from astronaut to auto mechanic, the right tools and access to the right people are essential.
During seminars I’ll ask, who has access to XYZ technology? Who has the availability of a physiatrist? Who has access to somebody who can do serial casting? Who has access to e-stim orthotics, or a particular splint or a partial weight supported trainer, etc.? Usually the same one or two or three people raise their hands. If the talk is in a hospital setting where all the clinicians are from that hospital they may all raise their hands. If it's a rural area where many are involved in skilled nursing or home health care, very few raise their hands.
Having access to and an understanding of a handful of technologies is essential to standard of care for stroke survivors. Also essential is access to clinicians with the right skill set. So what and who is essential? If I were to start "Pete's Center for Stroke Recovery" I would have access to the following before the doors ever opened.
Treadmills. Treadmills are never ending parallel bars. They expand the size of the gym with a very small footprint. Put a mirror in front of them and they become instantaneous feedback machines. They also provide an essential bit of quantifiable data: speed of gait.
Recumbent, 4-limb bilateral trainer. Recumbent trainers do not have to break the bank. Inexpensive ones can be found for $350 or so. These are essential not only as a pre-ambulation device, but also because they develop cardiovascular and muscular strength; "banking" both are essential to doing the hard work of recovery.
Some sort of harnessing system for gait training. Stroke recovery works best with over-challenge. Challenge drives neuroplasticity and neuroplasticity drives recovery. It's impossible to over challenge with standard gait training (a gait belt and guarding). The fear of falling on the part of the survivor and the therapist runs headlong into the challenge that needs to be realized. If the survivor is harnessed, falls are impossible and challenge flourishes. Partial weight sported walking is but one option that requires harnessing. Speed intensive treadmill training (also known as speed dependent treadmill training) has shown stellar efficacy in increasing speed of gait. The usual suspect in this category is the LiteGait. Over ground systems may be a better option for some gyms. NeuroGym, Biodex and other companies make over ground systems that provide an inexpensive harnessing option.
Cyclic electrical stimulation. The problem with e-stim generally is that the machines tend to intimidate most clinicians. But there are so many good things that e-stim dies that it is no longer optional. From reestablishing sensation to keeping soft tissue shortening at bay, e-stim is essential a certain points in the arc of recovery.
EMG based electrical stimulation (EMG-e-stim). This “next generation” of e-stim is important once a minute amount of movement is possible. It is believed that EMG-e-stim drives cortical changes which leads to small increases in movement. And small increases in movement are important in the early stages of repetitive practice paradigms.
Access to serial casting. Essential to fighting the good fight against soft tissue shortening. There are no splints that have shown clinical efficacy in increasing soft tissue length. Serial casting is the only nonsurgical treatment option to increase PROM of joints that have established contracture.
Access to neurologists, and especially physiatrists. Without them it's very difficult to deal with issues that range from spasticity to pain.
A constraint induced therapy (CIT) program. Although usually only benefiting higher-level stroke survivors, CIT is essential to the stroke recovery endgame.

Tuesday, December 28, 2010

Q and A.


My focus on stroke recovery has been near myopic for the last decade. I do professional talks and seminars, write general and coauthor journal articles about the subject. And there is also this blog. As you can imagine, all this writing attracts questions. I get questions from stroke survivors, caregivers and therapists. Many of the questions are heartbreaking but all of them are thought provoking. And I put a lot of effort into the answers.

Here are some examples...


The following question was from a 70-year-old M.D.

Q: I read with interest your wonderful work about spasticity and stroke. I suffered a stroke with left hemiplegia and spasticity about two years ago. I can walk slowly with a crane but I’m not very stable. Most annoying, however, is the spasticity in my elbow, wrist and fingers which is constantly flexed. The flexion increases during walking. I have weak dorsiflexion and severe plantarflexion of the big toe causing a shuffling gait. I am two years post; do you think there can be any improvement in gait and spasticity?

A: Thank you for the kind words about my work. Spasticity can only be reduced by reestablishing cortical control over the spastic muscles. Cortical control is reestablished through repetitive movement of the limbs. So, as much as you can move the arm, the better. Also, be careful not to let contracture set in. Because the joints of the arm are postured in the same place for a long periods of time (because of the spasticity) the cortical representation of those joints shrinks. Meanwhile, the soft tissue can also shrink. If enough soft tissue shrinkage has taken place this contracture can mean that no further gains can be made without surgery. So have an occupational or physical therapist develop a good and safe stretching program. Follow the program daily.

Also, consider electrical stimulation (ES). ES will move the joint through its range of motion--giving a good stretch. ES will also activate weak muscles, and ES has been shown to drive neuroplastic changes in the brain. Usually, once trained, you can do this at home, without a therapist. Generally the muscles that get ES are the weaker of the muscle groups (i.e. the finger/wrist extensors on the back of the arm.)

From a wife whose husband is ~ 1 year post stroke.

Q: I am always encouraging and try to be positive all the time; I ALWAYS say "WHEN you recover," never "IF you recover." Lately I wonder if I am just fooling him and me. EVERYTHING I read lately says global aphasia and apraxia have a very poor prognosis. Your book and your blog are very encouraging, but they do not address these issues very much.

A: Yes. You're right. And it is a major deficit in my book and in the generalized discussion about stroke recovery. "How do I know when I'm there?" How do we know when recovery has ended? I would start by making the argument that it's never ending. Because even if there is no further gains in terms of movement and communication, survivors still have to work hard just to tread water against the general decline of aging.

As you well know, your husband has had brain injury. I hate saying this because it seems like a cliché and a cop-out, but you have a new normal. And he has a new normal. Having said that, I wouldn't give up. I would keep going as much as you both can tolerate, but with plenty of vacations (from the struggle) and rest. You may find yourself settling into some sort of "maintenance program" as a hedge against natural effects of aging. But don't be afraid to pepper the maintenance program with new stuff as it comes into view.

And the truth be told, full recovery, as defined as fully the way the stroke survivor was prior to the stroke, almost never happens.

The following question was from a PT

Q: I just read your article “Using Gait Speed as a Marker for Progress” (advance for PT and rehab medicine, March 8, 2010). I was wondering if it is still a valid test if assistive devices are used. Thanks for sharing the information!

A: My understanding is that the validity is only without an assistive device. Look at it this way; let’s say somebody walks a given speed without an assistive device, and then walks faster with an assistive device. If you accept that gait speed is an overall health indicator, then the assistive device would somehow make them healthier. Probably not a valid assumption. Having said that, there may be some importance to increased gait velocity even with an assistive device. In other words, although a bit of an empirical leap, if, over time somebody is walking faster with a cane, that would be seen as a good thing. In clinical research the question of testing gait speed with or without the assistive device (or orthotic for that matter) always comes up. Generally, gait speed without any orthotic or assistive device as more indicative of a true baseline.

~

Tuesday, December 21, 2010

Game Yourself Bright

Over the years I've had a lot of questions about recovery of cognitive function. And it's difficult question because it's not my area. Or is it?


My Dad. Super smart.
(I was adopted.)


The word cognitive is quite broad. According to our smart uncle Wikipedia the word cognitive refers to the brain's ability to do any of the following:

Memory, association, concept formation, language, attention, perception, action, problem solving and mental imagery.

Whether you're learning how to move better or learning mathematics or French or whatever, the processes are similar. Both involve physical change within the brain. Both happen in the 1 to 3 mm cortex of the brain, and both involve repetitive challenging practice. There is no separation between "cognitive" and "motor learning." 

But Wikipedia has it wrong, or rather, incomplete. Movement and cognition are inexorably linked. There is a term for it: Motor cognition. People say, that's impossible. Movement is what dumb jocks do. But, again, motor learning is learning, and motor cognition is cognitive. Ironically, Wikipedia has a page on motor cognition.

I have another entry where I argue that great athletes have great minds. It involves the great Jim Thorpe, so you know its good.

I think what most people are talking about when they talk about cognitive function is the ability to think clearly. What is it that they say about intelligence? It's is the ability to keep two thoughts in your head at the same time-- something like that. I think a lot of stroke survivors lament the loss of part of their ability to think. Unfortunately, many people assume that stroke survivors necessarily have lost mental capacity. But, of course, many have not. I can't tell you how many people I know that have had a stroke and they're still smarter than me. "Unfair!" I might yelp if I was petty, which I'm not. (Unfair!)

So what can one do to develop an increase in, let's call it, "intellectual capacity"?
It may very well be video gaming. There are many in physical rehabilitation who love the idea of using the Wii for physical rehab. They call it Wiihabilitation, because, cute. There's actually some serious questions about whether these games actually help physical recovery. But can gaming help you remember where you put your keys? Can it help you "keep two thoughts in your head at the same time"? It turns out it can.In fact, there's a game that aims to do exactly that. It's call the N-Back. Find the actual game here. 


NOTE: Some games don't work at all. Find my take on Lumosity here. Gaming may not be the best way to boost cognition.

~

Monday, December 13, 2010

Speed is Good.


The ability to get from one place to another is essential to every animal. The speed at which travel takes place is an essential to determining the success or failure of everything from food acquisition to escaping danger. Gait requires input from the brain, spinal cord, peripheral nerves, muscular power, and joint and cardiovascular health.
Because of all these systems are required to coordinate gait, gait speed is an indicator of the health of many physiological systems. In all animals, gait speed decreases with age. In humans, the speed of our mobility is predictive of so much more than if we will eat, or are eaten.
What is remarkable about testing gait speed is how much it reveals about people. Here is a laundry list.
  • A decline in gait speed predicts a decline in attention
  • An increase in gait speed predicts a substantial decline in mortality while a decrease in gait speed predicts an increase chance of mortality
  • Gait speed correlates well with functional ability, future health status and the patient’s confidence in their balance
  • Gait speed predicts where discharge will take place (home, SNF, etc.), the chance of hospitalization, an increase in medical costs, disability and mortality
  • Gait speed predicts the need for rehabilitation
  • Gait speed can be used to determine the effectiveness of a particular rehabilitation treatment option.
  • Gait speed can be used as a surrogate for quality of gait; the faster the walking, generally speaking, the higher the quality of gait.
And much more!

Note: Walking speed is not only predictive of decline, it can also predict improvement. The faster the better.

Saturday, November 27, 2010

Friday, November 19, 2010

Make them walk funny and look lousy in shorts forever!

Warning: ENDING THE USE OF AN AFO CAN LEAD TO FALLS AND INJURIES.

Never
discontinue the use of an orthotic without first consulting the appropriate health care provider. Then call your doctor. Then have your doc talk to any other providers as needed. Then discuss it some more. Thank you.
It seems like a no-brainer. “Ted”, has hemiparesis and the classic signs of drop foot: Emerging spasticity in the super-strong muscles that push the foot down at the ankle. He also has a weakness of the muscles that lift the foot. On top of that, he has balance problems and weakness the muscles that stabilize the ankle. The safety imperative is intense. Everybody hates falls.
AFOs solve all of these problems and allow for an almost immediate functional gait. This allows stroke survivors to get on their feet, out the door and on with their life. AFOs work really well. They do the job. They allow survivors to be functional.
But “functional” sometimes collides with “recovery”.
What would recovery be in Ted’s case? Let’s define “recovery” as “progress towards being the same as prior to the stroke.” Will the AFO help or hurt recovery?
Consider what is happening in Ted’s brain. The area of stroke is infracted. This area is now devoid of living neurons and will soon be completely filled with cerebral spinal fluid. There is an area surrounding the infarct called the penumbra. This area is kept alive through anastomosis. Like cars going around a traffic jam by taking the back roads, blood cells are delivered through smaller, secondary vessels. This allows the neurons in the penumbra to stay alive--barely. 
But neurons in the penumbra have problems besides just a reduction in blood flow. The intense biological processes initiated by the stroke soaks the penumbric neurons in a metabolic soup. This further “stuns” the neurons.
That’s what’s happening in Ted’s brain. But what is happening in Ted’s life?
The PT's initial assessment of Ted’s gait is that there is a clear need for an AFO. Once the order is written, the AFO will take 2-3 weeks to fabricate. In the meantime therapists have begun gait training using an ace bandage tied to his lower leg. This forces the foot up and stabilizes the ankle. Ted is given a cane. Ted does well with this system and is able to walk 20 yards. He still fatigues easily, so a recumbent stepper is used to build cardiovascular strength.
Okay, now back to Ted’s brain. The neurons stunned by the stroke are starting to come back “on line”. The blockage has cleared in the primary artery. The metabolic soup that provided such a harsh environment for the neurons has dissipated. The neurons are ready to go back and do what they’ve always done; help Ted walk. But these neurons are never called upon.
They never will be.
Once the AFO arrives, Ted takes to it well. The gait training and cardio work he's done pays off. The AFO works so much better than the ace bandage that Ted immediately walks longer than he ever has. Ted is functional.
Meanwhile, the area of the cortex jam-packed full of neurons that control the ankle is shrinking. Rapidly. In a process known as learned nonuse the area will shrink to half its size in just a few weeks. Languishing for long enough will force the remaining neurons to migrate to some other task. Other neurons will go through "synaptic pruning" and they'll communicate less and less with the neurons around them. The muscles of that push the foot down may atrophy and will certainly shorten. The muscles that pull the foot up at the ankle are not called upon. The AFO does that work. The muscles that pull the foot up are small to begin with (relative to the muscles that push the foot down). And they begin to atrophy. Ted will have the AFO as a lifelong companion. The orthotic will substantially change his style of walking and may have future orthopedic implications.
What's the alternative? Managed care leaves few options and little time. Stroke survivors want to go home and their caregivers want them home. This is why AFOs seem like a blessing. 
      But a new perspective is emerging. There are researchers that advocate early electrical stimulation (e-stim) as a possible hedge against learned nonuse. E-stim has the potential to jump start movement, promote muscle building, calm spasticity and may even have an impact cortically. Repetitive practice with and without the help of robotics, gaming applications and task specific training may begin to bring the stunned cells of the penumbra back on line. A menagerie of emerging treatment options from mirror therapy to bilateral training to lower extremity constraint induced therapy also seem to have potential. But there are more flies in the ointment than ointment at this point. Research is far from definitive answers. One thing we do know is that the brain is a market economy. The “goods” (neurons) go to the “customers” (whatever movement is asked for). If nothing is asked of them neurons will find something else to do. As recovery is unmasked after stroke, every effort should be made to guide neurons “back home”. This will require more time to allow the arc of natural recovery to emerge. It will also require more focus on what is not easily seen: neuroplastic change in the brain. “Seeing” neuroplastic change requires sensitive, stroke-specific outcome measures.
    In other words, this shift in treatment philosophy, from “focus on functional” to “realizing recovery” is as much a work in progress for therapists as it is researchers.

Wednesday, November 10, 2010

What we do...

Here's a spankin' new flier from our lab. It gives a good overview of what we do.

Click on the images and then click again to make them larger!


Saturday, November 6, 2010

Seeing Stroke

Traditionally, the numbers for stroke have been written like this: "In the United States, 750,000 strokes per year. 500,000 new strokes, and the remaining 250,000 recurrent strokes." But by 2015 the estimate is well over 1 million per year. And here's where the stats get grim.

The "well over 1 million per year" bumps the number of recurrent strokes to over 300,000. For the five years after a stroke the chances of having another stroke are somewhere between 25 and 40%. So here's the question: do you know the symptoms of stroke? If you're stroke survivor, of course you do. Or do you? You might very well be an expert in the symptoms of stroke you HAD. But what if you have another one? Would you know the symptoms? So what are the symptoms that you're supposed to know? I work for the University of Cincinnati. They suggest the
FAST test. But its a mnemonic and here's some funny: I get confused about it even though I talk about it, a lot. I think, OK, FAST. What does the F stand for? Why Fast, of course, but yeah, not so much.

So what are the symptoms that stroke survivors should know? One way is to use the FAST test. FAST is based on the Cincinnati Prehospital Stroke Scale and National Institutes of Health Stroke Scale. FAST was developed by Rosie Miller, RN, a nurse who worked with The Greater Cincinnati / Northern Kentucky Stroke Team for 15+ years.

FAST stands for:

· FACE: Ask the person to smile. Do both sides of the mouth, elevate equally?

· ARMS: Ask the person to raise both arms. Do both arms lift equally?

· SPEECH: Ask the person to repeat a sentence. Are they able to repeat a sentence? Are the words slurred?

· TIME: If the person shows any of these symptoms of, call 911 or get to the hospital FAST.

Initiating treatment as soon as possible is vital because time saved is neurons saved. Every minute 2 million neurons and 14 billion synapses die.

It should be pointed out that there's some controversy about the FAST test. The FAST test is great because it is simple. And simple is good. If it's not simple people will forget what the letters stand for. But any test of signs and symptoms of an emerging stroke should be comprehensive enough to capture as many strokes in as possible. Which signs and symptoms to include is hotly debated. Even in the English-speaking world (US, UK, Canada, Australia and New Zealand) there is discrepancy over which and how many and which to include. Further, the wordings used in the various lists are inconsistent. Although there is little research to compare other ways of informing the public, the FAST test has been put to the test. Kleindorfer et al did a study in which they determined that the FAST test missed only about 8% of ischemic strokes but up to 30% of hemorrhagic strokes.

What else is typically included in tests other than the FAST test? Other tests include numbness, intense headache, vision issues, balance problems, loss of coordination, dizziness, difficulty swallowing, and confusion. Also included in some of the tests are the words "even if temporary" after the signs and symptoms. This is an attempt to capture transient attacks which often act as precursor warning signs of a full on stroke.

Consistency is essential to the success of communicating the symptoms and urgency of stroke to the general public. A single unified message increases the number of times it would be experienced by the general public. This would allow for more repetitive memorization of that consistent message. Again, however, there has been insufficient research to indicate which of the mnemonic devices is the most effective at capturing the most strokes.

But there may be a bigger question than what specific signs and symptoms to add. The question is: how do we best learn? Quick, answer this question: You see somebody that looks panicked and is holding their hand to their throat. What pathology does this represent? Here's another one: You see somebody clutching their chest. What is the pathology? While hardly comprehensive, the visual impact of these two examples is universally understood. The question is not what mnemonic is the best, but whether mnemonics are the best way. In my book, "Stronger After Stroke" (Demos 2008) I mention the Cincinnati Prehospital Stroke Scale. But I also suggest another way of memorizing the signs and symptoms of stroke: visualizing. Here's what I suggest:

The easiest way (to memorize the symptoms of stroke) is to start at the top of the head and move downward.

• Skull: Sudden, severe headache and/or dizziness with no known cause.

• Eyes: Sudden trouble seeing in one or both eyes.

• Face: Facial weakness.

• Ears: Sudden trouble understanding.

• Mouth: Sudden trouble speaking.

• Body: Sudden numbness, weakness or paralysis on one side of the body.

Stroke survivors have a much higher chance of having a second stroke than the general population has of having a first stroke. No matter what system you use, educate stroke survivors of the risk of recurrent stroke. And make sure they know as many signs and symptoms as possible
.

Saturday, October 2, 2010

Isn't there a machine for that?

I was over at dean's stroke musings a cool stroke recovery blog. He had a link to a study that showed that there were some changes in the brain when limbs are moved passively. Lets say you can't flex or extend your wrist. Will passively moving the wrist make it better? That is, if you move the "bad" wrist with your "good" hand, or have someone else move your wrist-- will that help the wrist move by itself? Will it change the part of the brain that controls the "bad" wrist? According to the study, there were brain changes. But. They didn't measure movement changes. Their bottom line: "These findings provide a potential neural substrate to account for alterations in motor and sensory function in stroke patients in response to long-term passive movement interventions." Which is a good point. Let's say you have a machine (which this study did) that moves the wrist back and forth, a half-hour per day. Would that help? Certainly those who make robotics like the Myomo (Val from our lab!) or the REO would have us believe that there are both brain changes and movement changes. There are many therapists who rely on hands-on techniques in which they "facilitate" movement by handling patients. The efficacy of those therapies remains questionable. But it may be a matter of dosage. If the machine can do it for a half hour (or 5 hours) at one joint, consistently, that's a little different than having a therapist do it for a 20 minutes at many joints. Also, robots (like the Myomo and REO) are very sensitive (using EMG or computers) to when the survivor needs help and when they don't. So that may make a big difference as well. Where does this leave the question "Does passive help?" So far as I can tell: moving the limb passively won't hurt and may help. Doing it with robotics seems to provide enough duration and specificity to provide measurable changes in movement. But the bottom line remains the same: Doing any movement yourself is always better than having someone else do it. So these options are for folks who have trouble moving the joint at all. Once you can move it with no help, it should be "all you." --

Monday, September 20, 2010

The upward spiral of recovery (II)


What tools are needed to allow for stroke survivors to drive their own recovery once they are discharged from therapy? It all starts with the home exercise program (HEP). Building the HEP should be initiated in the acute setting and continue to develop through subacute treatment. If the stroke survivor is unable to attend to an explanation of the arc of recovery and how the HEP fits into it, caregivers and family members may be educated instead. Once the stroke survivor is able to absorb the information, they would be the focus of education about the HEP. The amount of time recovering under the guidance of therapists is usually measured in months. The amount of time in which the patients is guiding their recovery is measured in decades. So the HEP becomes a flexible document.
The HEP should…
· Have the flexibility of progressing as the patient progresses
· Educate the patient on measuring progress
· Provide achievable milestones
· Provide benchmarks upon which the patient is directed back to therapy.
Upon discharge the HEP becomes an extension of the therapists’ and patients’ hard work. It's like teaching a kid to ride a bicycle. You hold them up, you run alongside, you guide them, and then you let go. We also tell our kids to keep pedaling because without the forward momentum, they fall. The HEP is the set of rules that will allow folks with brain injury continue their forward momentum. The hard work that patients have done with therapists is the first step on this upward spiral of recovery. But the HEP is the extension of that upward spiral. Finally, the patient fuse the HEP with their own plan of recovery that incorporates their own life. The life they lead drives recovery.
Therapists have to discharge patients once the patient has “plateaued.” However, research from many disciplines has refuted the concept of the definitive plateau. Any therapist worth their salt knows that recovery can continue, sometime spontaneously, well beyond the point of discharge. Unfortunately, the calculus made by many brain injured folks is simple: therapist=recovery. So part of the job of the therapist is to explain that recovery from brain injury is not just the plateau that precipitated discharge from subacute therapies. In fact, recovery becomes a lifelong series of plateaus.
Therapists are paid to be optimists. They know that focusing on disability is less effective than focusing on potential. Medical doctors have to low-ball any prognosis. Doctors feel uncomfortable setting expectations too high. An optimistic prognosis not realized goes against the medical ethics dictum; “first, do no harm.” If doctors set expectations too high, patient frustration (along with some pointed feedback) will be close behind. Therapists, on the other hand, have the responsibility of making clear the potential level of recovery. While doctors low-ball, therapists imagine. The act of transferring that imagination from therapist to patient is the proverbial "Apple a day."

Friday, September 3, 2010

The Upward Spiral of Recovery

There is a common suggestion among many in the "alternative medicine" industry expressed in the question: "If it means less business, why would your doctor want you to be healthy?” A strict emphasis on healthy lifestyle including diet and exercise would be like the proverbial "Apple a day" – keeping the doctor away. Doctors who do this – who keep themselves away as much as they can – are the best doctors. And therapists who "keep themselves away" are the best therapists.

Many pathologies allow for a definitive discharge point. The patient who has had a knee replacement gets therapy, and then goes home to live the rest of his life. But neurological disorders are different. Many, from Parkinson's to multiple sclerosis, are progressive. But what of non-progressive neurological disorders like stroke and traumatic brain injury? Does this "Apple a day" philosophy work? Is there a point at which these populations no longer need therapists?

Many patients with acquired brain injury believe that they will always need therapists. Most see therapists as essential to the recovery process, no matter how long (months, years, decades) it takes for them to achieve their highest level of potential recovery. But this view is incorrect.

There is a point at which therapists are no longer the fulcrum for recovery. Nor should they be for reasons that range from financial to practical. At discharge stroke survivors are, and should be, in complete control of their own recovery. During the chronic phase of recovery from stroke, the speed of recovery slows. In the chronic stage the physiological action of recovery is based on a lot of self-directed hard work.

Much of what is required is relatively simple, and revolves around the broad concept of repetitive practice. In order to take charge, stroke survivors need the tools to initiate and follow an "upward spiral of recovery.” This term is used to describe the path to the highest level of potential recovery. The "upward spiral of recovery" is driven by real-life demands for everything from coordination to cardiovascular strength.

Thursday, August 12, 2010

brainu

Exercise, does it help after stroke? Of course it does, but the word exercise is so broad it's darned near meaningless.

One of the things that's confusing is the way that clinicians have historically used the word exercise. They have almost always meant "doing a movement against resistance." The focus is generally on muscle building. But, although they're weakened, the muscles of stroke survivors are usually strong enough to do whatever. And the peripheral neurology is still intact. All the nerves outside of the brain injury are doing just fine.
So the question becomes, why all the emphasis on muscle building?

The muscles are working. What's not working is the brain. Can exercise be directed at the brain? Yup. But the emphasis should come off of muscle strengthening and onto repetitive practice.
Part of the confusion is that both kind of exercises (muscle building and repetitive practice) crossover. For instance, just working on muscle building will also drive some changes in the brain. Conversely, repetitive practice of movement will build muscle. Another thing that adds confusion is that fatigue is such a huge issue among stroke survivors. So exercise for the sake of building muscle (as well as cardiovascular exercise) is important. Still, the emphasis should be on the brain. I suppose you could simplify it as that old athletic training saying: "Less weight, more reps." Sort of. For more clarity please see this article.

Tuesday, July 27, 2010

Rockin' Recovery


I'm here in Finland, above the Arctic Circle, the home country of my wife, Aila. We're visiting for 3 weeks.

This is a great country for clearing one's head. The things that matter to "us" seem to trouble them less. Their perspective has changed my perspective!

There is a particular study the Fins have done on stroke recovery that has caught my eye several times over the past few years. Part of it is that any study that says "stroke" and "Finland" will get my attention. Part of it is that music is so personally important. The following quote comes from this article.

"A daily dose of one’s favorite pop melodies, classical music or jazz can speed recovery from debilitating strokes, according to a study published recently. When stroke patients in Finland listened to music for a couple of hours each day, verbal memory and attention span improved significantly compared to patients who received no musical stimulation, or who listened only to stories read out loud, the study reports.

Those exposed to music also experienced less depression than the other two control groups.

Three months after a stroke, verbal memory was boosted by 60 percent in music listeners, by 18 percent in audio book listeners, and by 29 percent in non-listeners, according to the lead author Teppo Sarkamo, PhD, a neuroscientist at Helsinki University in Finland.

The differences held true after six months as well, says the study, which is published in a recent issue of the journal, Brain. Sarkamo’s findings bolster a growing body of research pointing to the benefits of music and music therapy for conditions including autism, schizophrenia, and dementia. But this is the first time music alone has been shown to have a positive effect on victims of brain injury, such as stroke, he says.

“Everyday music listening during early stroke recovery offers a valuable addition to the patients’ care, especially if other active forms of rehabilitation are not yet feasible,” Sarkamo says."

Also, this systematic review seems to further indicate music can help in a number of ways.

`

Thursday, July 15, 2010

It's the whole enchilada.

Stroke. The leading cause of long-term disability. It's not the leading cause of short-term disability. That's probably headache or back pain. And it's not, like, the fifth leading cause of long-term disability. It is the LEADING cause of LONG TERM disability. It's the big kahuna. It's the whole enchilada.
 
Figure stroke recovery out and it will inform you about everything that the brain does. Insights into cortical plasticity? Done. Recovering after dramatic brain injury. Done. Learning? Done.

Here's some irony:

There is only one treatment option for recovery from stroke that has the same level of testing as any drug on the shelf of a drugstore. One. Constraint induced therapy (CIT).


So you would think that every rehab hospital would do CIT. But, not so much.


Part of the problem is the foggy perception that many clinicians have about what CIT is. Read this article, and then have your therapist read it.

~

Thursday, June 24, 2010

It's okay. I speak aphasic.


You're the first responder to a serious car accident. You try to talk to one of the two people in the car - the only one that's conscious. But everything that she desperately tries to tell you seems to trip on her tongue. Is she in shock?


A house is burning down and you are a firefighter. You need to make quick decisions about whether to send your crew inside the burning house. A woman outside the house is desperately trying to tell you something. But... can't... quite...


The Drake Center in Cincinnati Ohio is having a training session for first responders on how to communicate with folks with expressive aphasia. Please click on the flyer, below.


Note that the address of the Drake center is:

151 W. Galbraith Rd.

Cincinnati, OH 45215

Please e-mail me if you have any questions...


Blog Archive
